
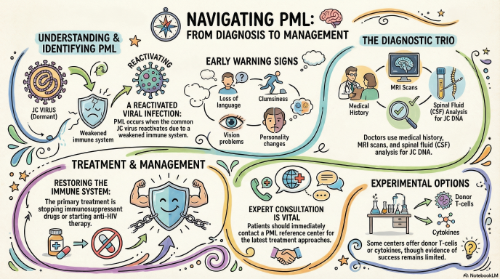
Progressive multifocal leukoencephalopathy (PML) is a rare and serious disease of the central nervous system (CNS) caused by the JC polyomavirus (JCV), commonly known as JC virus. It primarily affects the brain and can cause progressive neurological disability.
PML occurs when JCV, which is usually kept under control by the immune system, becomes able to infect cells of the central nervous system. This is most often associated with significant impairment of cellular immunity. However, the circumstances in which PML develops are complex, and the disease can occur in people with different underlying conditions.
PML is a rare complication even among people who are at increased risk. Understanding why some people develop PML while others with JCV infection do not remains an important area of research.
The JC Virus and PML
JCV is extremely common in the general population. Studies indicate that antibodies against JCV are found in a large proportion of adults, meaning that many people have been exposed to the virus at some point in their lives. After the initial infection, JCV can remain in the body in a persistent or latent state without causing illness in most people.
Having been infected with JCV does not mean that a person will develop PML.
The important difference is what happens when the immune system is no longer able to control the virus effectively. In certain circumstances, JCV can reactivate and reach the central nervous system. There, particular viral variants can acquire changes that enable them to infect brain cells, including oligodendrocytes, the cells responsible for producing myelin.
The exact sequence of events leading from an otherwise silent JCV infection to PML is still not completely understood. Researchers are studying the interaction between the virus, the immune system, and individual genetic factors to understand why PML develops in some people but not others.
Who Is at Risk of Developing PML?
PML is most strongly associated with conditions or treatments that impair cellular immunity.
It can occur in people with:
- HIV infection, particularly when significant immune suppression is present;
- Hematological malignancies, including some lymphomas and leukemias;
- Organ or stem-cell transplantation, where immunosuppressive treatment may be required;
- Autoimmune or inflammatory diseases treated with certain immunosuppressive or immunomodulatory medications;
- Multiple sclerosis, particularly in association with some disease-modifying treatments such as natalizumab;
- Certain primary or acquired immune deficiencies;
- Other situations in which the immune system is significantly impaired.
PML associated with medications has become an increasingly recognized issue because some therapies that modify or suppress the immune system can alter the body’s ability to control JCV. Drug-associated PML has been reported with a number of immunosuppressive or immunomodulatory treatments, and the level of risk varies according to the specific drug and the patient’s individual circumstances.
Importantly, PML is not limited to people with HIV or multiple sclerosis. It can occur in association with malignancies, transplantation, immune deficiencies, autoimmune and inflammatory diseases, and some cancer or immune-modifying treatments.
For patients and families, understanding the underlying cause of immune impairment can be an important part of understanding why PML developed.
How Does PML Affect the Brain?
The name progressive multifocal leukoencephalopathy describes some of the characteristic features of the disease.
Progressive refers to the fact that neurological symptoms can worsen over time.
Multifocal means that several areas of the brain can be affected.
Leukoencephalopathy refers to disease affecting the brain’s white matter, particularly areas containing myelin.
JCV infection damages cells involved in maintaining myelin, interfering with the normal communication between different parts of the nervous system. The areas affected can vary considerably from one person to another. This is one reason why the symptoms of PML can be so different between patients.
Symptoms of PML
There is no single pattern of symptoms that identifies PML.
Early symptoms depend largely on which areas of the brain are affected and how extensive the lesions are. Symptoms usually develop over days or weeks rather than appearing as a single sudden event, although the clinical course can vary.
Possible symptoms include:
- Difficulty speaking or finding words;
- Problems understanding language;
- Weakness or loss of coordination;
- Difficulty walking or maintaining balance;
- Changes in vision;
- Problems with fine motor movements;
- Cognitive changes, including difficulties with attention or memory;
- Changes in the ability to perform familiar tasks;
- Personality or behavioral changes;
- Sensory symptoms;
- Seizures in some cases.
Symptoms may initially be subtle. A person may notice that something is wrong without being able to explain exactly what has changed.
As PML progresses, neurological difficulties can become more pronounced and may affect mobility, communication, vision, cognition, independence, and the ability to perform everyday activities.
Because early symptoms can resemble those of other neurological conditions, including stroke, tumors, inflammatory diseases, or other infections, recognizing PML early can be challenging.
Diagnosing PML
Diagnosis usually involves combining several pieces of information rather than relying on a single test.
Doctors may consider:
- The person’s medical and treatment history;
- The presence of conditions associated with impaired immunity;
- Neurological examination;
- Magnetic resonance imaging (MRI) of the brain;
- Examination of cerebrospinal fluid (CSF) for JCV DNA using polymerase chain reaction (PCR);
- And, in selected difficult cases, additional investigations or brain biopsy.
MRI plays an important role because PML often produces characteristic patterns of white-matter abnormalities. Detection of JCV DNA in CSF can provide strong evidence for the diagnosis, although a negative PCR does not always exclude PML, particularly in some early or inflammatory cases.
For this reason, when clinical suspicion remains high, doctors may need to continue investigating even when an initial test does not provide a definitive answer.
PML and the Immune System
The relationship between PML and the immune system is central to understanding the disease.
In most people, the immune system keeps JCV under control. When cellular immunity becomes severely impaired, this control can be lost. JCV may then reactivate, undergo changes that favor infection of the central nervous system, and cause the brain infection associated with PML.
This also explains why restoring effective immune control of JCV is central to current PML management. The appropriate approach depends on why the person’s immune system has become impaired.
For someone with HIV, for example, effective antiretroviral therapy can restore immune function and is a fundamental component of PML management. In drug-associated PML, reducing or stopping the responsible immunosuppressive treatment may be considered when medically appropriate, although this decision can be complex and must take into account the underlying disease and the risks of changing treatment.
PML-IRIS
Restoring immune function is essential, but the recovering immune response can sometimes create another complication.
PML-IRIS, or PML-associated immune reconstitution inflammatory syndrome, occurs when the recovering immune system mounts a strong inflammatory response against JCV-infected areas of the brain.
This inflammation can temporarily worsen neurological symptoms or produce new symptoms, even though the underlying goal of immune recovery is beneficial.
PML-IRIS is particularly recognized in people with HIV after starting effective antiretroviral therapy and can also occur in other settings, including some cases associated with immunomodulatory treatment. Its recognition and management can be complex and require specialist assessment.
Importantly, not every worsening after immune restoration is necessarily PML-IRIS, and treatment decisions need to be based on the individual clinical and radiological situation. Recent expert guidance emphasizes careful assessment of inflammatory features and immune recovery rather than assuming that corticosteroids or other interventions are appropriate in every case.
Treatment of PML
There is currently no universally effective antiviral treatment that directly eliminates JCV from the brain.
The cornerstone of treatment is therefore to restore or improve the immune response against JCV whenever this can be safely achieved. The specific strategy depends on the underlying cause of immune impairment and the individual clinical situation.
Depending on the circumstances, management may involve:
- Starting or optimizing antiretroviral therapy in people with HIV;
- Reducing or discontinuing an immunosuppressive or immunomodulatory treatment when medically appropriate;
- Managing complications such as PML-IRIS;
- Intensive neurological and rehabilitation support;
- And, in selected circumstances, considering investigational immune-based therapies.
Several experimental approaches are being studied, including immune checkpoint inhibitors and JCV-specific T-cell therapies. Some studies and case series have reported encouraging outcomes in selected patients, but these approaches remain investigational and the evidence is not yet sufficient to consider them established treatments for PML.
This is an important distinction: promising research is not the same as a proven treatment.
Because PML is rare and patients differ substantially in their underlying conditions and immune status, developing and testing treatments is particularly challenging. Continued research is needed to determine which approaches can safely improve outcomes and for whom.
Prognosis and Recovery
PML remains a potentially life-threatening disease, but its outcome is not the same for everyone.
Prognosis depends on many factors, including the underlying cause of immune impairment, the degree of immune recovery, how early PML is recognized, the extent and location of brain involvement, and the person’s overall health.
Some people experience severe neurological disability, while others achieve substantial stabilization and recovery. Even when the infection is controlled, however, neurological damage may leave lasting difficulties.
Recovery can therefore continue long after the acute phase of the disease. Rehabilitation may involve physiotherapy, occupational therapy, speech and language therapy, cognitive rehabilitation, psychological support, and adaptations to everyday life.
For some survivors, recovery is measured not only by medical tests but by returning to activities that once seemed ordinary: walking more safely, communicating more easily, preparing a meal, returning to work, going outside independently, or reconnecting with other people.
Living With PML
The end of active disease does not necessarily mean the end of the PML journey.
Some survivors live with long-term neurological consequences that can affect mobility, balance, vision, speech, cognition, independence, employment, relationships, and emotional wellbeing.
For this reason, PML should not be viewed only as an acute medical event. For many people, it becomes a long-term process of rehabilitation, adaptation, and rebuilding everyday life.
The needs of a person with PML may also change over time. Someone who initially requires intensive medical and nursing support may later need rehabilitation, psychological support, assistance at home, workplace adaptations, or help regaining independence.
PML Is Rare, But It Is Not One Single Story
PML is a complex disease with different causes, different presentations, and very different outcomes.
The experience of a person with HIV-associated PML may be very different from that of someone who developed PML after treatment for multiple sclerosis, cancer, an autoimmune condition, transplantation, or another form of immune impairment.
For this reason, individual stories are important, but they should not be used to predict what will happen to another person.
There is still much that researchers and clinicians do not know about PML. At the same time, understanding of the disease has advanced considerably, particularly in the areas of diagnosis, immune mechanisms, neuroimaging, and immune-based approaches to treatment.
Research continues to explore ways of detecting PML earlier, understanding why JCV becomes pathogenic, restoring effective antiviral immunity, and developing treatments that can directly or indirectly control the infection.
For patients and families, this means that PML remains a serious diagnosis, but the story does not end with the diagnosis. Medical treatment, rehabilitation, support, and research all have a role to play in determining what comes next.