
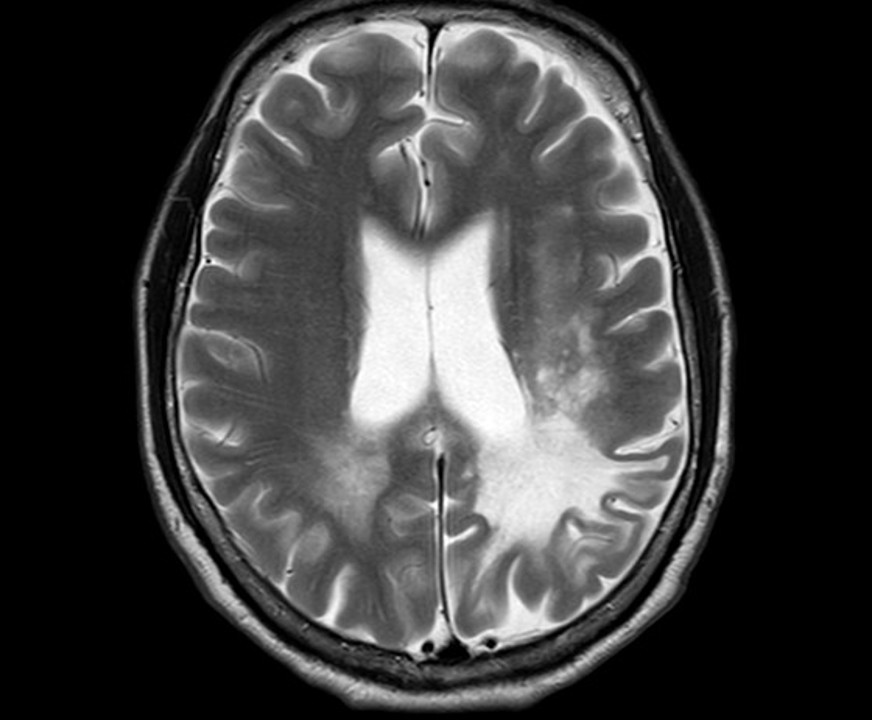
Diagnosing progressive multifocal leukoencephalopathy (PML) can be challenging. The symptoms may resemble those of other neurological conditions, and because PML is rare, it may not initially be considered among the possible diagnoses.
Early recognition is important because PML can progress rapidly, and the opportunity to restore immune control of JC virus (JCV) may be time-sensitive. At the same time, diagnosing PML requires careful evaluation because there is no single test that can identify every case with complete certainty.
A diagnosis is usually based on the combination of the person’s clinical history, neurological symptoms, brain MRI findings, immune status, and laboratory testing for JCV.
When Should PML Be Suspected?
PML should be considered when a person with significant immune impairment develops new, progressive neurological symptoms, particularly when those symptoms evolve over days or weeks rather than appearing suddenly.
The symptoms can vary greatly depending on which areas of the brain are affected. They may include:
- Weakness or clumsiness, particularly on one side of the body;
- Difficulty walking or maintaining balance;
- Problems with speech or finding words;
- Difficulty understanding language;
- Changes in vision;
- Problems with coordination or fine motor movements;
- Cognitive or memory difficulties;
- Changes in behavior or personality;
- Sensory disturbances;
- Seizures in some cases.
These symptoms are not specific to PML. Similar problems can occur with stroke, brain tumors, multiple sclerosis, other infections, inflammatory diseases, and several other neurological conditions.
This is one reason why PML can sometimes be difficult to recognize at the beginning.
The Importance of the Medical History
The first step is usually a detailed medical history and neurological examination.
The healthcare team will want to understand:
- When the symptoms started;
- Whether they are progressing;
- Which functions have changed;
- Whether symptoms appeared suddenly or gradually;
- Whether the person has a condition that affects the immune system;
- Which medications or treatments they are receiving or have recently received;
- Whether there is a history of HIV infection, cancer, transplantation, autoimmune disease, multiple sclerosis, or another condition associated with impaired immunity.
Medication history is particularly important because PML can occur in association with several immunosuppressive or immunomodulatory treatments.
The combination of a compatible clinical picture and a relevant risk factor can significantly increase the suspicion of PML.
Brain MRI
Magnetic resonance imaging (MRI) of the brain is one of the most important investigations when PML is suspected.
PML typically produces abnormalities in the brain’s white matter. The location and pattern of these lesions can provide important clues to the diagnosis.
MRI can also help distinguish PML from other neurological conditions and can show how the disease changes over time.
However, MRI findings should always be interpreted together with the clinical history and other investigations. Not every white-matter lesion is PML, and not every person with PML will have exactly the same MRI pattern.
In some cases, particularly early in the disease, the MRI findings may be subtle. When clinical suspicion remains high, further investigation and follow-up imaging may therefore be necessary.
Cerebrospinal Fluid and JCV PCR
A lumbar puncture can be performed to obtain cerebrospinal fluid (CSF), the fluid surrounding the brain and spinal cord.
The CSF can then be tested for the presence of JCV DNA using polymerase chain reaction (PCR).
Detection of JCV DNA in the CSF, together with a compatible clinical and MRI picture, can provide strong evidence supporting a diagnosis of PML.
However, a negative JCV PCR does not always exclude PML.
JCV DNA may be present at very low levels, particularly in some early cases or in people whose immune system is already mounting a response against the virus. The sensitivity of the test can also depend on the laboratory method used.
Therefore, if the clinical and MRI findings remain strongly suggestive of PML, doctors may consider repeating the CSF examination or using a more sensitive assay, rather than automatically abandoning the diagnosis.
This is an important point for patients and families: one negative test does not necessarily provide the final answer when the overall clinical picture remains concerning.
Does a Brain Biopsy Need to Be Done?
In most cases, a brain biopsy is not the first diagnostic step.
A biopsy involves obtaining a small sample of brain tissue and examining it for characteristic pathological changes and evidence of JCV infection. Because it is an invasive procedure with potential risks, it is generally reserved for situations in which the diagnosis remains uncertain despite other investigations.
A biopsy may sometimes be considered when:
- MRI findings are atypical;
- CSF testing remains negative;
- Another diagnosis remains possible;
- Or establishing a definitive diagnosis is important for treatment decisions.
The decision must be made by an experienced medical team after considering the potential benefits and risks.
PML Is a Diagnosis That May Require Reassessment
PML does not always present in a textbook way.
In some people, symptoms are initially attributed to another neurological condition. In others, the first MRI may be interpreted as suggesting a different diagnosis. A patient may also have more than one condition that can produce neurological symptoms.
For this reason, the diagnosis may sometimes require repeated clinical assessment, additional MRI examinations, repeat CSF testing, or consultation with specialists experienced in PML.
If PML remains a possibility despite inconclusive initial investigations, continuing to investigate can be important.
Seeking Advice From a PML-Experienced Center
Because PML is rare and complex, patients with a confirmed diagnosis—or with a strong clinical suspicion—may benefit from consultation with a medical center or specialist team with experience in PML.
This can be particularly important when:
- The diagnosis is uncertain;
- The JCV PCR is negative despite suggestive findings;
- MRI findings are difficult to interpret;
- The person has multiple possible causes of immune impairment;
- The patient is receiving immunosuppressive or immunomodulatory treatment;
- Treatment decisions are complex;
- Or an investigational therapy is being considered.
A specialist center can also help coordinate neurology, infectious diseases, immunology, neuroradiology, rehabilitation, and other areas of care when necessary.
What Happens After a Diagnosis?
Once PML has been diagnosed, attention usually turns to the underlying cause of immune impairment and to restoring effective immune control of JCV whenever this is possible.
There is currently no universally effective antiviral drug that directly eliminates JCV from the brain. Consequently, treatment is primarily directed at restoring or improving the immune response against the virus.
The appropriate approach depends on the individual situation.
HIV-associated PML
For people with HIV, starting or optimizing effective antiretroviral therapy is a fundamental part of treatment because it can allow the immune system to recover and regain control over JCV.
PML associated with immunosuppressive or immunomodulatory treatment
When PML is associated with a medication that suppresses or modifies the immune system, the medical team may consider stopping, reducing, or changing that treatment when it is medically appropriate.
This decision is not always simple. The underlying disease may itself require ongoing treatment, and abruptly changing an immunosuppressive therapy can carry risks.
For this reason, such decisions should always be made by the treating specialists.
Other causes of immune impairment
In some people, immune suppression cannot simply be stopped or reversed. This may occur in certain cancers, congenital or acquired immune deficiencies, transplantation, or conditions such as idiopathic CD4 lymphocytopenia.
In these situations, management may be particularly complex and may require consultation with specialists in infectious diseases, neurology, hematology, immunology, or other relevant fields.
PML-IRIS: When Immune Recovery Causes Inflammation
Restoring the immune response is an essential part of managing PML, but immune recovery can sometimes produce an intense inflammatory reaction.
This condition is known as PML-associated immune reconstitution inflammatory syndrome (PML-IRIS).
PML-IRIS can occur when the recovering immune system reacts strongly against JCV-infected areas of the brain. Neurological symptoms may temporarily worsen, and MRI scans may show increased inflammation or other changes.
PML-IRIS is particularly recognized in people with HIV after starting effective antiretroviral therapy, but it can occur in other situations involving immune recovery.
Recognizing PML-IRIS can be difficult because worsening neurological symptoms may also represent progression of PML itself.
For this reason, new or worsening symptoms during immune recovery require prompt medical assessment.
Are There Drugs That Directly Treat PML?
Many drugs have been investigated or used in individual patients over the years in an attempt to inhibit JCV or improve the immune response.
Some, including mirtazapine, mefloquine, and cidofovir, have been used in the past based largely on laboratory findings, biological hypotheses, or individual case reports.
However, these drugs have not demonstrated convincing clinical benefit in controlled studies and are not established treatments for PML. Some may also carry significant risks or toxicities.
This is an important distinction because individual reports of apparent improvement can sometimes create the impression that a treatment has been proven when it has not.
Patients and families should discuss any proposed treatment with a medical team familiar with PML, particularly when the treatment is experimental or is being used outside its established indication.
Experimental and Investigational Therapies
Research into PML continues, including approaches designed to strengthen the immune response against JCV.
Some investigational strategies include:
- JCV-specific T-cell therapies, in which immune cells capable of recognizing JCV are prepared and administered to the patient;
- Immune checkpoint inhibitors, which are drugs originally developed for cancer treatment and may enhance certain immune responses;
- Approaches involving immune-modulating molecules such as interleukin-7;
- And other strategies aimed at restoring or enhancing JCV-specific immunity.
Some studies and case series have reported encouraging results in selected patients. However, these approaches remain investigational, and evidence is still insufficient to establish them as universally effective treatments for PML.
Because PML is rare and patients have very different underlying conditions, conducting large clinical trials is difficult. Participation in an experimental treatment should therefore be discussed with an experienced specialist center, with a clear understanding of the potential benefits, uncertainties, and risks.
Why Early Recognition Matters
There is no simple test that can diagnose every case of PML at an early stage.
Nevertheless, early clinical suspicion can make a difference.
When a person at risk develops new, progressive neurological symptoms, considering PML early may lead to faster MRI evaluation, appropriate CSF testing, and specialist consultation.
The earlier the underlying immune problem is recognized and addressed, the greater the opportunity may be to prevent further progression and limit neurological damage.
This does not mean that every suspected case will turn out to be PML. It means that PML should remain part of the diagnostic conversation when the clinical circumstances make it plausible.
Prognosis and Recovery
The outcome of PML varies considerably between individuals.
Important factors include:
- The underlying cause of immune impairment;
- The person’s immune status;
- How quickly effective immune control can be restored;
- The extent and location of brain involvement;
- The severity of neurological symptoms at diagnosis;
- And the person’s overall health.
Some people stabilize and recover substantial function. Others are left with significant neurological disability, and in severe cases PML can be fatal.
Even when the infection is brought under control, recovery of the nervous system may take a long time. Some neurological damage may be permanent, while other functions may improve gradually through spontaneous recovery and rehabilitation.
For survivors, therefore, treatment does not necessarily end when the infection is controlled.
Physiotherapy, occupational therapy, speech and language therapy, cognitive rehabilitation, psychological support, and practical adaptations may all become important parts of the longer-term recovery process.
A Diagnosis Is the Beginning of a Journey
Receiving a PML diagnosis can be overwhelming. Patients and families may suddenly have to understand an unfamiliar disease, make decisions about treatment, deal with uncertainty, and adapt to changes in everyday life.
It can help to remember that the diagnosis is not the same thing as a prediction of one person’s future.
PML can follow very different courses, and individual outcomes cannot be determined from the diagnosis alone.
For someone who has been diagnosed with PML, useful questions for the medical team may include:
- What is the likely underlying cause of the PML?
- What do the MRI findings show?
- Has JCV been detected in the CSF?
- If the JCV PCR is negative, how confident are we in the diagnosis?
- Could another condition explain the symptoms or MRI findings?
- Can the underlying immune impairment be reversed or reduced?
- Is there a risk of PML-IRIS?
- Should the case be discussed with a specialist PML center?
- What rehabilitation and supportive care should begin now?
- Are there clinical trials or investigational approaches for which the patient might be eligible?
Patients and caregivers should feel able to ask these questions and to request clarification when something is not understood.